Vector-borne disease patterns are not changing because pathogens have suddenly become more virulent. They are changing because the ecological and infrastructural conditions that determine where vectors survive, reproduce, and transmit are being systematically altered by climate change. This article examines that alteration as a structural determinant of health system failure. It is written for readers who already understand that health systems are complex adaptive systems, not mechanical delivery pipelines. If you are looking for a listicle of “climate diseases,” stop reading. If you want to understand why surveillance systems built for stationary risk maps are failing, and what implementation science can and cannot do about it, continue.
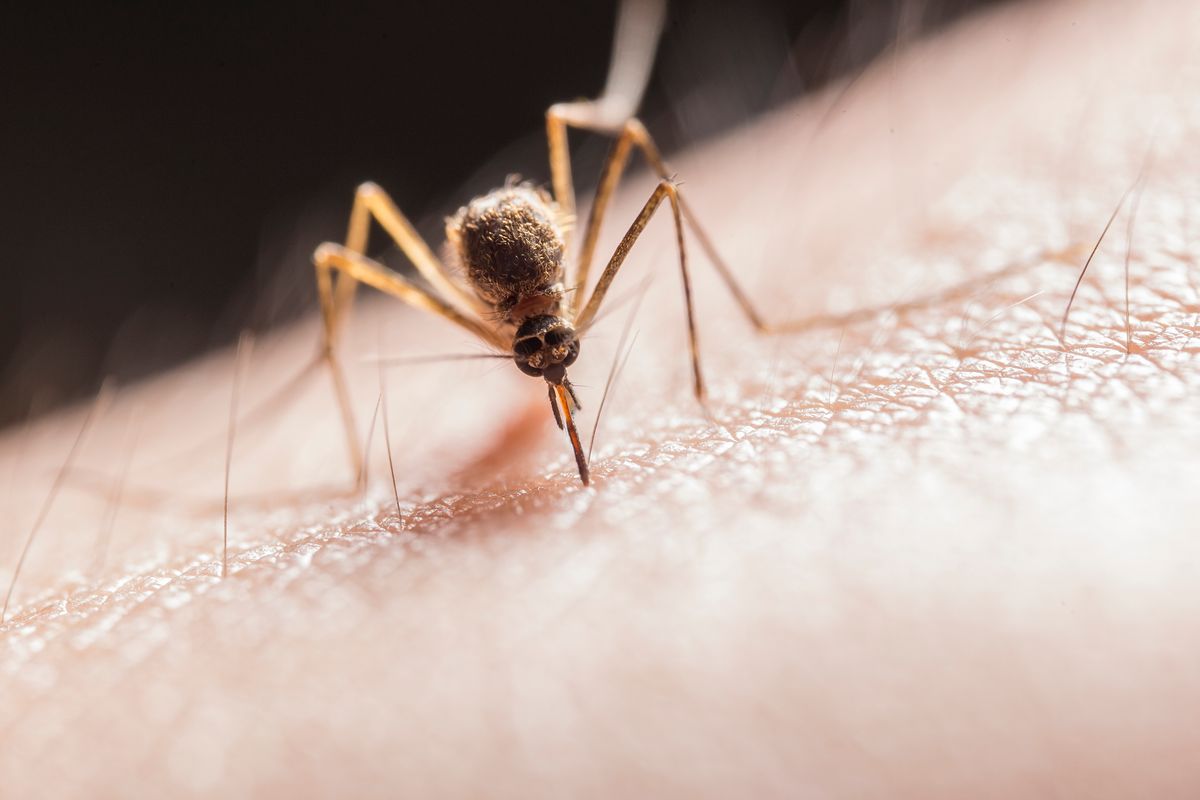
Three concepts anchor this analysis. First, vectorial capacity — the mathematical expression of a vector population’s ability to transmit a pathogen, incorporating vector density, biting rate, extrinsic incubation period, and vector survival. Second, ecological niche shift — the movement of the climatic envelope within which a vector species can complete its life cycle. Third, surveillance lag — the temporal gap between a change in vectorial capacity on the ground and the detection of that change by public health institutions. Climate change acts on all three simultaneously, and health systems are largely organized to respond to none of them.
This is not a climate science article. It is a health systems article. The question is not whether Aedes albopictus will reach new latitudes. The question is why the institutions responsible for detecting and responding to that expansion are structurally incapable of doing so in time.
The Political Economy of a Moving Risk Map
Most national vector-borne disease programs are built around static risk maps. These maps are produced through periodic entomological surveys, then converted into resource allocation decisions: where to spray, where to place sentinel traps, where to train clinicians, where to stock diagnostics. The maps are treated as infrastructure. They are embedded in procurement cycles, staffing plans, and interagency agreements. When the underlying ecology shifts, the maps do not shift with it. They become artifacts of a previous climate.
This is a political economy problem, not a data problem. Updating a risk map is technically straightforward. The barrier is that the map is load-bearing. It holds up budgets, job descriptions, laboratory supply chains, and political accountability structures. Changing the map means changing who gets funded, who gets blamed, and who gets credit. In most systems, no single actor has both the authority and the incentive to initiate that change. The result is a form of institutional hysteresis: the system remains locked in a previous state even after the conditions that justified that state have disappeared.
Climate change accelerates this failure by increasing the rate at which ecological conditions diverge from institutional assumptions. A risk map produced in 2015 may have been accurate for the climate of 2005. By 2025, it is a historical document. But the institutions that produced it are still operating as if it were a live operational tool.
Vectorial Capacity Is a Systems Variable, Not a Species Trait
To understand why this matters, we need to be precise about what is changing. Vectorial capacity is not a fixed property of a mosquito or tick species. It is an emergent property of the interaction between vector biology, pathogen biology, and environmental conditions. Temperature affects the extrinsic incubation period — the time required for a pathogen to complete development inside the vector and become transmissible. Humidity affects vector survival. Rainfall patterns affect breeding site availability. Land use change affects human-vector contact rates. All of these are climate-sensitive.
The operational implication is that a vector species can be present in a region for years without causing significant transmission, then become a major public health threat when a threshold is crossed. That threshold is not a single number. It is a configuration of temperature, humidity, precipitation, and human settlement patterns. When climate change shifts that configuration, transmission can emerge in places with no historical experience of the disease, no clinical familiarity, no laboratory capacity, and no public awareness.
This is the structural failure point. Health systems are designed to respond to known diseases in known places. They are not designed to detect the emergence of known diseases in unknown places. The distinction is critical. A dengue outbreak in Bangkok is a management problem. A dengue outbreak in Buenos Aires is a systems failure. The pathogen is the same. The institutional response capacity is not.

Surveillance Lag as a Structural Determinant of Failure
Surveillance lag is the interval between the moment a change in vectorial capacity becomes detectable and the moment a health system acts on that detection. It has three components:
- Detection lag: The time required for surveillance systems to register a signal. This is determined by the spatial distribution of sentinel sites, the frequency of sampling, and the sensitivity of diagnostic tools.
- Interpretation lag: The time required for the signal to be recognized as meaningful. This is determined by the analytical capacity of public health institutions and their willingness to override prior assumptions.
- Response lag: The time required to mobilize resources once a signal has been interpreted. This is determined by budgeting cycles, procurement processes, and political decision-making.
Climate change increases all three. Detection lag increases because sentinel sites are placed according to historical risk maps, not current ecological conditions. Interpretation lag increases because clinicians and epidemiologists in newly affected areas do not have the experiential knowledge to recognize atypical presentations. Response lag increases because the institutional machinery for vector control, clinical training, and public communication does not exist in areas with no prior history of the disease.
The total surveillance lag for a newly emerging vector-borne disease in a non-endemic area can be measured in years. That is not a failure of individual competence. It is a structural property of systems that are organized around stationary assumptions in a non-stationary world.
Implementation Science Confronts Its Own Limits
Implementation science — the study of methods to promote the uptake of evidence-based interventions into routine practice — has a role here, but it is a constrained one. The field has developed strong frameworks for understanding barriers to implementation: the Consolidated Framework for Implementation Research, the Theoretical Domains Framework, the Reach, Effectiveness, Adoption, Implementation, Maintenance framework. These frameworks are useful for diagnosing why a given intervention does not scale. They are less useful when the problem is not the implementation of a known intervention but the absence of an intervention to implement.
Climate-driven vector-borne disease emergence is a problem of anticipatory adaptation. The intervention is not a specific technology or protocol. It is a capacity: the ability to detect, interpret, and respond to ecological signals before they become epidemiological emergencies. Implementation science has historically been weak on capacity-building as an outcome. It prefers interventions with clear boundaries, measurable fidelity, and defined endpoints. Anticipatory adaptation has none of these. It is a continuous process, not a discrete program.
This is not a criticism of implementation science. It is a statement of scope. The field was developed to solve the problem of evidence-practice gaps in stable systems. Climate change is making the systems themselves unstable. That requires a different set of analytical tools — ones drawn from complexity science, institutional theory, and political economy — in addition to, not instead of, implementation science.
Case Example: Dengue in Southern Europe
Southern Europe provides a useful case study. Aedes albopictus, the Asian tiger mosquito, has been established in parts of Italy, France, and Spain since the 1990s. For two decades, its presence was treated as an entomological curiosity rather than a public health priority. Local transmission of dengue was considered unlikely because the climatic conditions were assumed to be marginal. That assumption was reasonable under the climate of the late twentieth century. It is no longer reasonable.
In 2023, Italy reported locally acquired dengue cases in multiple regions. France reported locally acquired cases in 2022 and 2023. Spain reported its first locally acquired dengue case in 2018. These are not large outbreaks by global standards. But they are significant as signals. They indicate that the ecological conditions for local transmission now exist in areas where they did not exist a generation ago. The question is whether health systems in these areas are organized to detect and respond to that signal.
The answer is mixed. Some regions have strengthened entomological surveillance and clinician education. Others have not. The variation is not random. It tracks the same political economy dynamics described above: regions with stronger public health infrastructure and more recent experience with vector-borne disease are more likely to invest in anticipatory capacity. Regions without that experience are more likely to wait for a confirmed outbreak before acting. That waiting is rational from a short-term budgeting perspective. It is catastrophic from a systems perspective.
The Institutional Design Problem
What would a health system designed for climate-driven vector-borne disease emergence look like? It would have three properties that most current systems lack.
First, it would treat surveillance as a continuous adaptive process, not a periodic data collection exercise. This means integrating entomological, climatological, and epidemiological data streams in real time, and using that integration to update risk assessments continuously. The technical tools for this exist. The institutional arrangements do not. Most surveillance systems are organized around fixed reporting cycles and fixed geographic units. They are not designed to detect signals that cross administrative boundaries or emerge between reporting periods.
Second, it would build response capacity in advance of need. This means training clinicians in non-endemic areas to recognize vector-borne diseases, stocking diagnostics in laboratories that have never processed a dengue or chikungunya sample, and establishing vector control protocols before the first case appears. This is politically difficult because it requires spending money on problems that have not yet occurred. It is also the only approach that reduces surveillance lag to clinically meaningful timescales.
Third, it would create institutional mechanisms for updating risk maps without triggering political blame cycles. This is the hardest requirement. Risk map updates are politically charged because they imply that previous resource allocations were wrong. No institution wants to admit that. The solution is not to depoliticize the process — that is impossible — but to create regular, expected, low-stakes update mechanisms that do not require a crisis to trigger. Think of it as the difference between a scheduled software update and an emergency patch. The former is routine. The latter is a sign of failure.
What This Means for Health System Researchers
For researchers working at the intersection of implementation science, complexity, and health policy, climate-driven vector-borne disease emergence is a natural experiment in institutional adaptation. It offers a way to study how health systems respond — or fail to respond — to slow-moving environmental change. The key variables are not clinical. They are institutional: the structure of surveillance systems, the distribution of authority over risk assessment, the incentives facing public health leaders, and the feedback loops between ecological signals and institutional action.
This is a research agenda that requires methodological pluralism. Quantitative models of vectorial capacity are necessary but insufficient. They tell us what is happening ecologically. They do not tell us why institutions are not responding. For that, we need qualitative and mixed-methods work: case studies of surveillance system adaptation, comparative analyses of institutional responses to vector range expansion, and process evaluations of anticipatory capacity-building efforts. The field of implementation science has the tools for this work. It needs to apply them to a new class of problems.
The stakes are not abstract. Every year of surveillance lag in a newly affected area represents preventable morbidity and mortality. The people who will suffer most are those in health systems with the least anticipatory capacity — which is to say, the systems that can least afford to fail.
Frequently Asked Questions
Why are vector-borne diseases appearing in places with no prior history of them?
Because the ecological conditions that determine vector survival and pathogen transmission are shifting. Temperature, humidity, and precipitation patterns are changing in ways that expand the geographic range within which vectors like Aedes albopictus and Aedes aegypti can complete their life cycles and transmit pathogens. The vectors are not migrating in a coordinated way. They are finding that places that were previously too cold, too dry, or too variable are now suitable. When that happens, the pathogens they carry can establish local transmission cycles in human populations that have no prior immunity and no clinical experience with the disease.
What is surveillance lag, and why does it matter?
Surveillance lag is the time between a change in disease transmission conditions and the detection of that change by public health institutions. It matters because every unit of lag represents time during which transmission can occur undetected. In a newly affected area, surveillance lag is typically longer than in endemic areas because sentinel sites are not positioned to detect the signal, clinicians are not trained to recognize the disease, and laboratories are not equipped to confirm it. Reducing surveillance lag is the single most important intervention for limiting the health impact of climate-driven vector-borne disease emergence.
Can implementation science help address this problem?
Yes, but with caveats. Implementation science provides frameworks for understanding why evidence-based interventions do or do not reach routine practice. Those frameworks are useful for diagnosing barriers to anticipatory adaptation. However, the problem of climate-driven vector-borne disease emergence is not primarily a problem of implementing a known intervention. It is a problem of building institutional capacity to detect and respond to signals that have not yet occurred. That requires extending implementation science beyond its traditional focus on discrete interventions and toward the study of adaptive capacity in complex systems.
What should health system leaders do now?
Three things. First, integrate entomological, climatological, and epidemiological data streams into a continuous surveillance process rather than a periodic reporting exercise. Second, build clinical and laboratory capacity for vector-borne disease diagnosis in areas that are ecologically suitable but historically non-endemic. Third, create routine, low-stakes mechanisms for updating risk maps so that resource allocation can track ecological change without requiring a crisis to trigger it. None of these are technically difficult. All of them are institutionally difficult. That is the point.
Next Steps for This Publication
This article is the first in a planned series on climate-sensitive health system failure. The next piece will examine the political economy of vector control programs in middle-income countries, with a focus on how budgeting cycles create structural barriers to anticipatory investment. A third piece will analyze the role of private sector actors — particularly pest control companies and diagnostic manufacturers — in shaping the institutional response to vector range expansion. If you have questions or case material relevant to these topics, the editorial team welcomes correspondence.